
Can Low Thyroid Cause High Cholesterol? What to Check First
Low thyroid function is one of the most common causes of high cholesterol. Thyroid hormone sets the rate at which the body converts cholesterol into steroid hormones and bile acids. When thyroid output drops, that conversion slows and cholesterol accumulates in the blood. Cardiology guidelines themselves list hypothyroidism as a secondary cause to rule out before treatment begins, yet in practice that step is often skipped.
My approach is to find and address the cause of a health issue rather than suppress the number it produces. This article walks through the thyroid connection, how the definition of high cholesterol has changed since the 1980s, what the statin trial data shows for people without heart disease, and the natural strategies that support healthy lipid metabolism.
Key Takeaways
- The liver produces most of the cholesterol in your blood regardless of diet. The body uses it to build cell membranes, vitamin D, bile acids, and steroid hormones.
- Active thyroid hormone (T3) drives the conversion of cholesterol into those hormones and bile acids. When conversion slows, cholesterol rises. This is why hypothyroidism is a recognized secondary cause of high cholesterol.
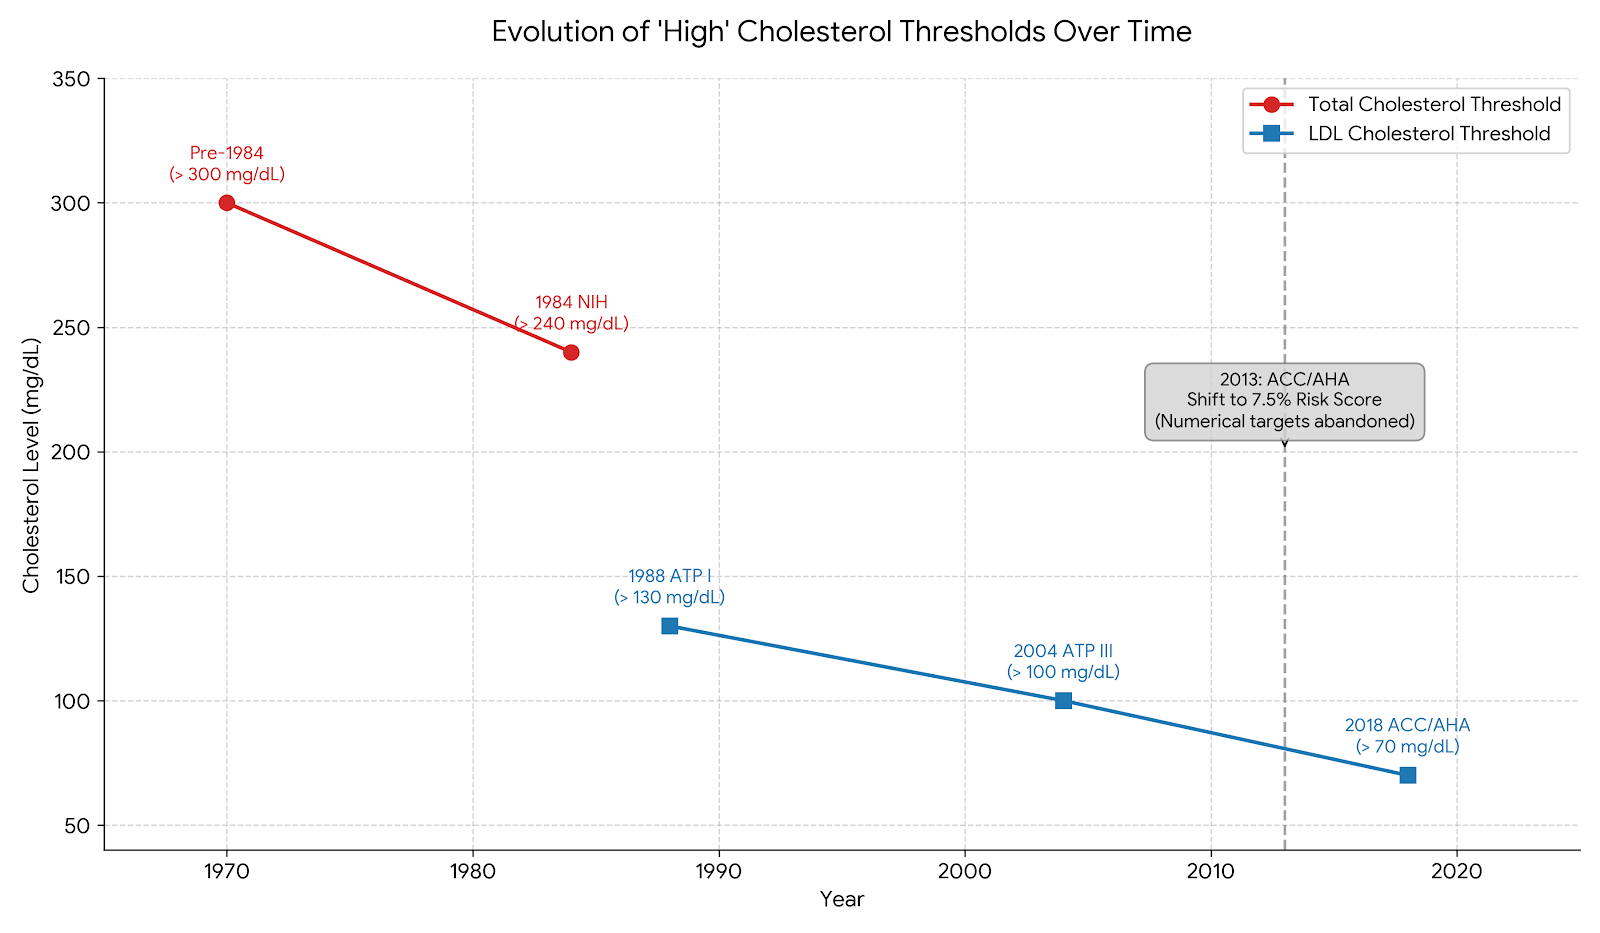
- The lab threshold for "high" total cholesterol dropped from roughly 300 mg/dL before 1984 to 240, then 200 became the ideal. Each revision expanded who qualified for treatment.
- A 2010 meta-analysis of 65,229 people without prior heart disease found no significant reduction in death from any cause with statin treatment over an average of 3.7 years.
- Never stop or change a prescribed medication on your own. Investigate root causes together with your provider.
This article is educational and does not replace care from a qualified provider. I am a certified clinical herbalist, not a physician. Anyone with established heart disease, and anyone taking prescription medication, should make treatment decisions with their doctor.
How the Thyroid Controls Cholesterol
Evidence: strong. The link between hypothyroidism and elevated cholesterol appears in standard physiology and in cardiology guidelines as a secondary cause to rule out before treatment.
Cholesterol is a substance your body manufactures on purpose. It forms the structural backbone of every cell membrane and serves as the raw material for vitamin D. It is also the precursor to cortisol, estrogen, testosterone, and progesterone. Your liver produces the majority of the cholesterol in your blood no matter what you eat.
The thyroid governs how quickly that cholesterol gets used. Converting cholesterol into steroid hormones and into bile acids (the digestive fluids that also carry cholesterol out of the body) requires adequate active thyroid hormone, called T3. When thyroid output is low, the conversion stalls and cholesterol accumulates in the blood while it waits. Elevated cholesterol in this context signals that the body cannot use the cholesterol it has.
This connection has a long clinical history. Dr. Broda Barnes spent over 50 years studying thyroid dysfunction and reviewed roughly 70,000 autopsy records from Graz, Austria. He also ran a multi-decade observational series in his own practice. In his 1976 book he reported that patients whose low thyroid function was treated with natural desiccated thyroid suffered heart attacks at a small fraction of the rate the Framingham Heart Study data predicted for a comparable group. His series was uncontrolled, so it counts as clinical observation rather than trial evidence, and he considered it the central finding of his career. The biologist Dr. Ray Peat (1936 to 2022) built on this work. He explained how thyroid hormone drives the conversion of cholesterol into hormones and bile, and he argued that the polyunsaturated fatty acids in common vegetable oils suppress thyroid function. Barnes estimated that 40% or more of the population had undiagnosed low thyroid function, and if he was close to right, that would account for a large share of the high cholesterol readings doctors see today.
How the Definition of High Cholesterol Changed
Evidence: documented. Every threshold change described below is recorded in the published guidelines themselves.
The threshold for "high" cholesterol has been lowered several times since the 1980s, and each revision classified more people as needing treatment. Millions now take cholesterol-lowering drugs while heart disease remains a leading cause of death, which is reason enough to look at how the numbers moved.
Before 1984: the statistical average era
Doctors mainly looked at total cholesterol, and labs generally used 300 mg/dL as the cut-off for high. The average middle-aged American measured between 210 and 240 mg/dL, and that was considered the healthy norm. Cholesterol rising with age was accepted as normal physiology. The 1984 NIH Consensus Development Conference changed this, declaring anything over 240 mg/dL high and setting 200 mg/dL as the new ideal.
1988 to 2004: the treat-to-target era
The National Cholesterol Education Program's Adult Treatment Panel guidelines shifted focus to LDL targets. Across three iterations, the LDL goal dropped from under 130 to under 100 as optimal, with an under-70 target for high-risk patients.
2013: the risk calculator
The American College of Cardiology and the American Heart Association abandoned numerical targets in favor of a 10-year cardiovascular risk score. A calculated risk of 7.5% or higher triggered a statin recommendation regardless of the actual LDL number, unless LDL sat at or above 190.
2018 to present: the hybrid approach
The current guideline blends the risk calculator with LDL thresholds. The 7.5% score still decides who starts a statin, while numbers like under-70 returned for people with existing heart disease to decide when treatment intensifies.
Common Signs of Low Thyroid Function
Evidence: moderate to strong. This list combines symptom descriptions published by the NIH and CDC with the clinical records of Dr. Broda Barnes and the writing of Dr. Ray Peat. High cholesterol belongs on the list itself.
Thyroid hormone regulates the metabolic rate of nearly every cell, so low function shows up across the whole body in recognizable clusters.
- Metabolic: a low waking temperature (below 97.8°F by Barnes' method, described below), cold hands and feet, weight gain that resists a caloric deficit, high cholesterol, and a slow resting pulse.
- Physical: dry skin, brittle hair, thinning of the outer third of the eyebrows, an orange tint to the palms from carotene the liver cannot convert, puffiness in the face or ankles (called myxedema), or an enlarged thyroid gland (a goiter).
- Energy, mood, and cognition: deep fatigue that sleep does not fix, brain fog, poor short-term memory, and low mood.
- Digestive and reproductive: constipation, sluggish digestion, heavy or irregular periods, elevated prolactin, fertility struggles, and frequent infections.
Other Root Causes of High Cholesterol
Evidence: moderate to strong, varying by mechanism. Insulin resistance and liver dysfunction are well documented drivers of lipid changes; the others rest on established physiology.
Thyroid function is the largest factor, and it is rarely the only one. Each cause below points toward a fix that addresses the source rather than the lab value.
- Chronic inflammation. The liver increases cholesterol production during inflammation because cholesterol is transported to sites of tissue damage for repair. Resolving the inflammation removes the demand.
- Poor liver function. The liver is the hub of cholesterol metabolism. Alcohol, medications, environmental toxins, and fatty liver all impair its ability to regulate lipids.
- Chronic stress. Cortisol is made from cholesterol, so sustained stress increases production. Elevated cortisol also drives insulin resistance and suppresses the conversion of T4 into active T3, compounding the thyroid problem.
- Insulin resistance. When cells resist insulin, the liver produces more VLDL particles. Triglycerides rise and protective HDL falls, while LDL shifts toward the smaller, denser type most associated with cardiovascular risk.
- Nutrient shortfalls. Magnesium, vitamin D, folate, and vitamins B6 and B12 all participate in healthy lipid and homocysteine metabolism.
- Gut dysbiosis. Beneficial gut bacteria help recycle bile acids, which are made from cholesterol. An imbalanced microbiome impairs that clearance. Low-fiber diets and antibiotic overuse are common contributors.
What the Statin Evidence Shows
Evidence: contested. Trial data exists on both sides. This section cites the primary literature raising doubts about primary prevention, meaning treatment of people who have not had a heart attack or stroke.
Statins block HMG-CoA reductase, the enzyme the liver uses to make cholesterol. They are the default prescription for an elevated lipid panel. The trial record for people without existing heart disease deserves a closer look than it usually gets.
A meta-analysis published in the Archives of Internal Medicine pooled 11 randomized controlled trials covering 65,229 participants without prior cardiovascular disease. Over an average treatment period of 3.7 years, statin therapy did not significantly reduce death from any cause. Later analyses by Diamond and Ravnskov documented how trial results in this field are typically reported as relative risk reductions, which makes small absolute differences appear large. When the same data is expressed as absolute risk, the benefit for a person without heart disease is modest.
The side effects deserve equal attention. Reported effects include muscle pain and weakness, memory complaints, elevated liver enzymes, an increased risk of type 2 diabetes, and peripheral neuropathy. The brain also depends on cholesterol. It holds roughly a quarter of the body's total supply and uses it to build synapses. No direct causal link between statins and cognitive decline has been proven, and it remains a reasonable open question given how the drug works. For further independent analysis, I point readers to the writing of The Midwestern Doctor, a practicing physician who publishes anonymously.
None of this means statins are never appropriate. For people with established cardiovascular disease or very high risk, the trial data is stronger and the decision belongs with a qualified provider. This article is about investigating causes first, especially for people with moderately elevated numbers whose thyroid function, inflammation markers, insulin sensitivity, and liver health have never been examined. Do not stop or change a prescribed medication on your own.
Checking Thyroid Function at Home
Evidence: historical clinical practice. The temperature method comes from Barnes' published work. It has not been validated in a modern trial, and it does not replace lab testing.
Doctors typically rely on a TSH blood test, which measures the pituitary signal to the thyroid rather than how well thyroid hormone works inside cells. Many people produce enough T4, the inactive storage form, without converting enough of it into active T3 in their tissues. Standard bloodwork can miss that shortfall. Dr. Barnes used basal body temperature as a practical functional indicator, and it costs nothing to check.
The Barnes basal temperature method
- Use a sensitive thermometer. A basal body temperature thermometer works best, kept on your nightstand so you can reach it without getting up.
- Measure the moment you wake. Place it under your arm for 10 minutes before you move or speak. Activity raises your temperature and voids the reading. Barnes noted that premenopausal women get the most accurate result on the second or third day of menstruation.
- Track for at least two weeks. Barnes considered a waking underarm temperature at or below 97.8°F, alongside symptoms, a strong signal of low thyroid function. If yours runs consistently low, bring the log to a provider willing to test beyond TSH. Free T3 and Free T4 alongside thyroid antibodies give a fuller picture.
Ray Peat used a related method. He tracked pulse rate and temperature together, before and after breakfast, charted over at least two weeks, on the grounds that the pair reveals more than either measure alone. He also wrote that he never met anyone with a TSH above 2 who was comfortably healthy, a far lower bar than the standard reference range.
What suppresses the thyroid
Peat argued that the body downregulates thyroid function as a protective response to stress and to a perceived shortage of energy. The contributors he identified fall into a few groups.
- Dietary: polyunsaturated seed oils and oxidized fish oils (see my cooking oils guide and fish oil article), very low-carb or fasting regimens, excess estrogen and soy phytoestrogens, low protein intake, large amounts of raw goitrogenic vegetables, excess iodine, and fluoride.
- Lifestyle: prolonged endurance exercise, chronic psychological stress, too little sunlight, and poor sleep, all of which raise cortisol and slow metabolism.
- Toxins: bacterial endotoxin from sluggish digestion, mold and mycotoxins, heavy metals, and pesticides.
Natural Strategies for Healthy Lipid Metabolism
Evidence: mixed. The dietary foundations rest on established metabolic physiology. The herbs carry long traditional use, with supporting trials of varying size and quality.
Once you have a sense of the cause, these foundations do most of the work. Herbs work best layered on top of them.
Diet and lifestyle foundations
- Support the thyroid. Reduce polyunsaturated vegetable oils and ensure adequate iodine, selenium, zinc, and vitamin A. Coconut oil supports metabolic rate without the thyroid burden Peat attributed to PUFAs.
- Eat whole foods. Wild-caught fish, pastured eggs, grass-fed meats, fruit, root vegetables, and well-cooked greens, with stable fats like butter and ghee. Soluble fiber from foods like oats and apples binds bile acids and promotes cholesterol excretion. Minimize seed oils and refined, ultra-processed food.
- Support the liver and sleep. Reduce alcohol and unnecessary toxin exposure. Aim for at least 7 hours of sleep, and build daily stress relief into the schedule, such as breathwork or a walk outside.
- Move and balance blood sugar. Moderate exercise improves insulin sensitivity and raises HDL. Eat protein and fiber alongside starches and sugars to avoid the glucose spikes that drive VLDL production. Favor strength work over long endurance cardio.
Herbs herbalists reach for
These are the plants and compounds I see used most for lipid and metabolic support in clinical herbalism. Work with a qualified herbalist or provider on selection and amounts, because several interact with prescription medications, including blood thinners and diabetes drugs.
- Berberine: a plant alkaloid found in barberry, goldenseal, Oregon grape, and several other plants, and among the most studied natural compounds for lipid and blood sugar metabolism. It interacts with many medications.
- Artichoke leaf: a traditional bitter that stimulates bile flow. Bile is the body's main route for excreting cholesterol, so sluggish liver function is its natural fit.
- Celery seed: used traditionally for blood pressure and fluid balance, with research interest in its compound 3-n-butylphthalide.
- Hawthorn: a cornerstone cardiovascular tonic with centuries of use across European herbalism.
- Garlic: culinary and medicinal cardiovascular support, best studied in its aged form.
- Milk thistle: the classic liver-protective herb, useful when the liver needs support to clear cholesterol efficiently.
- Fenugreek: a seed rich in soluble fiber and saponins, used traditionally for both lipid and blood sugar support.
Thyroid Support Options
Evidence: the prescription options below are standard medicine with decades of use. The over-the-counter options rest on traditional use and user reports, including my own.
If you and your provider determine your thyroid is low, restoring it often brings cholesterol down on its own as the body resumes converting it into hormones and bile. What follows is an educational overview to discuss with your doctor rather than a treatment plan. I am a clinical herbalist, not a physician.
One caution belongs up front. Taking thyroid hormone or glandular products when you are not hypothyroid, or taking more than your body needs, can cause heart palpitations, arrhythmia, insomnia, and bone loss. Products containing T3 act fast and are the easiest to overshoot, so get a proper diagnosis and provider oversight before starting any of them. If your thyroid has been removed or is severely damaged, supplements will not replace a prescription.
Over-the-counter support
Progest-E is a progesterone preparation dissolved in vitamin E that appears throughout Peat's work as a way to oppose excess estrogen, which can bind thyroid hormone and keep it from working. It is a hormone rather than a thyroid medication, and it belongs in a conversation with a provider who understands it. Reported effects include drowsiness and cycle changes.
Thyroid+ from Heart & Soil is a nose-to-tail supplement made from freeze-dried grass-fed bovine thyroid plus liver and kidney. It is what I take for the mild hypothyroidism I developed after years living in a house with black mold. As a food-based supplement, its active hormone content is not standardized, which is worth knowing before you buy. My experience has been consistent bottle to bottle. If you want to try it, this is my referral link (I earn a commission on purchases made through it, at no extra cost to you).
Prescription options to discuss with your doctor
- Levothyroxine (Synthroid and generics): synthetic T4 with a long, steady half-life and decades of use as the standard of care. It contains only T4, so people who convert poorly to T3 may still feel hypothyroid despite normal labs. Inexpensive and widely prescribed.
- Natural desiccated thyroid (Armour, NP Thyroid): derived from porcine thyroid and containing both T4 and T3. Many people who felt poorly on T4-only report improvement on NDT because it supplies active hormone directly. Pigs produce a higher T3-to-T4 ratio than humans, so it can cause a T3 surge, and some conventional endocrinologists decline to prescribe it while many primary care and functional doctors will. I wrote more on the proposed FDA action on NDT.
- Liothyronine (Cytomel): pure synthetic T3, sometimes added alongside levothyroxine for people who convert T4 poorly. Its short half-life means dosing is usually split through the day, and it carries the highest risk of hyperthyroid symptoms when the amount is even slightly too high. It is most often managed by an endocrinologist or a functional medicine doctor.
Frequently Asked Questions
Can low thyroid cause high cholesterol even with a healthy diet?
Yes. The liver makes most of your cholesterol regardless of what you eat. When low thyroid function slows the conversion of cholesterol into hormones and bile acids, it accumulates in the blood no matter how clean the diet is. If dietary changes have not moved your numbers, the thyroid is the first thing to investigate.
What waking temperature suggests low thyroid?
Dr. Broda Barnes considered a normal waking basal temperature to be 97.8°F to 98.2°F, measured under the arm for 10 minutes before rising. A reading consistently at or below 97.8°F, alongside symptoms, was his signal of low thyroid function and his cue to test further.
Do statins prevent death in people without heart disease?
The pooled trial data says the effect on death from any cause is not significant in that group. A meta-analysis of 11 randomized trials covering 65,229 people without prior cardiovascular disease found no significant mortality reduction over an average of 3.7 years. For people with established heart disease, the evidence is stronger.
Should I stop my statin if I think my thyroid is low?
No. Never stop or adjust a prescribed medication on your own. Bring your temperature log and symptoms to your doctor, request a full thyroid panel with Free T3 and Free T4 plus antibodies, and make any medication decision together based on the results.
To go deeper, explore my other writing on cholesterol and metabolic health, or book an educational consultation to talk through your own situation.
- Barnes BO, Barnes CW. Solved: The Riddle of Heart Attacks. Robinson Press, 1976.
- Barnes BO, Galton L. Hypothyroidism: The Unsuspected Illness. Harper & Row, 1976.
- Peat R. "Cholesterol, longevity, intelligence, and health." raypeat.com.
- Peat R. "Thyroid: Therapies, Confusion, and Fraud." raypeat.com.
- National Institute of Diabetes and Digestive and Kidney Diseases (NIH). "Hypothyroidism (Underactive Thyroid)." Cited for the standard symptom descriptions in the signs section.
- Ray KK, Seshasai SR, Erqou S, et al. "Statins and all-cause mortality in high-risk primary prevention: a meta-analysis of 11 randomized controlled trials involving 65,229 participants." Archives of Internal Medicine. 2010;170(12):1024-1031. doi:10.1001/archinternmed.2010.182
- Diamond DM, Ravnskov U. "How statistical deception created the appearance that statins are safe and effective in primary and secondary prevention of cardiovascular disease." Expert Review of Clinical Pharmacology. 2015;8(2):201-210. doi:10.1586/17512433.2015.1012494
- National Institutes of Health. "Lowering Blood Cholesterol to Prevent Heart Disease." Consensus Development Conference Statement, 1984. Cited as the historical record of the threshold change.
- Grundy SM, Stone NJ, et al. "2018 AHA/ACC Guideline on the Management of Blood Cholesterol." Circulation. 2019;139(25). Cited as the record of current thresholds.
